Operating theatres are high-pressure systems where clinical care, staffing, equipment, and time collide. A delayed first case can quickly disrupt every procedure scheduled afterward. Nurses may prepare instruments while anaesthetists manage urgent clinical changes. Surgeons need reliable access to people, rooms, and technology. Patients need safety, dignity, and clear communication throughout the experience.
What are common challenges in operating theatre management? The answer usually includes unpredictable emergency cases, staff shortages, inefficient room turnover, incomplete documentation, equipment failures, and competing surgical priorities. These problems are connected. A missing implant can extend turnover time. Poor handover can create avoidable risks. Even a five-minute delay may affect recovery beds, transport, and evening staffing. Small disruptions matter.
Dr Atul Gawande, surgeon, author, and public health researcher, wrote, “No matter how expert you may be, well-designed checklists can improve outcomes.” His observation reflects a practical truth in theatre management. Expertise alone cannot control a complex operating environment. Standardised briefings, visible schedules, equipment checks, and respectful teamwork provide structure. Still, checklists are not magic. They can become routine paperwork when teams stop thinking critically. That is an uncomfortable weakness worth examining.
Effective management therefore requires more than improving theatre utilisation figures. Leaders must balance productivity with patient safety, staff wellbeing, and clinical judgment. They need accurate data, but also direct conversations with theatre teams. Numbers may show a late start. They may not explain exhaustion, unclear instructions, or poor coordination. Understanding these challenges requires experience, evidence, and a willingness to question established routines.
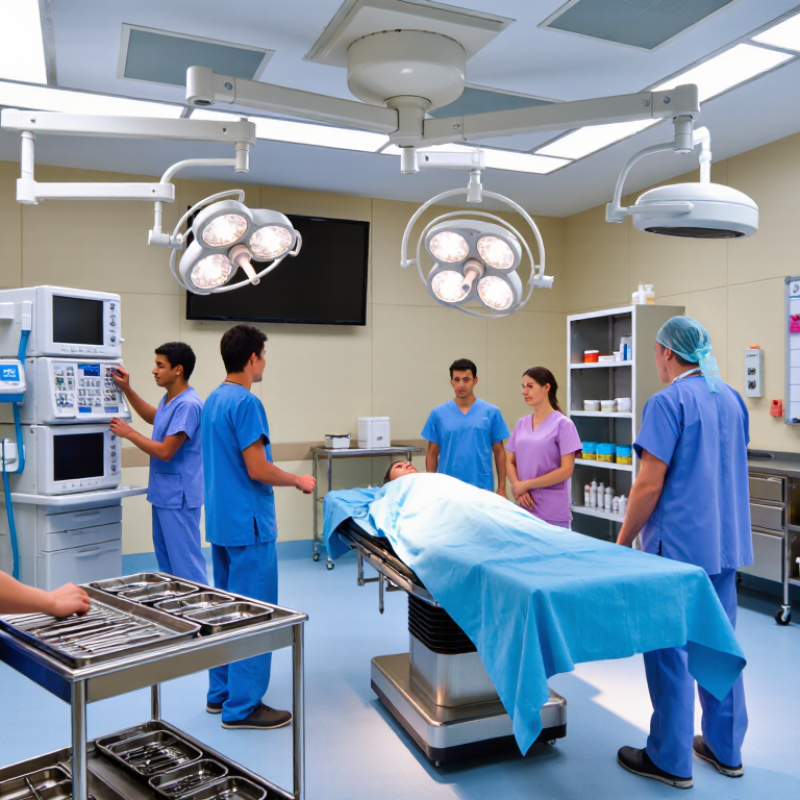
Operating theatre management is more than filling an electronic schedule. It connects patient need, clinical readiness, staff capability, equipment, infection prevention, and financial control. At 07:30, the manager may verify consent, anesthesia assessment, instruments, implants, blood availability, and recovery capacity. One missing item can delay every later case. The scope includes daily coordination, escalation, workforce planning, quality governance, and learning from near misses.
Safety must sit inside productivity, not beside it. The WHO Surgical Safety Checklist study, published in 2009 across eight hospitals, found complications fell from 11.0% to 7.0% after implementation. Mortality declined from 1.5% to 0.8%. This supports the manager’s role in enforcing briefings, sign-outs, and clear ownership. The WHO Global Patient Safety Action Plan 2021–2030 reports harm affects about one in ten healthcare patients. It identifies more than half as preventable. These figures make incident review and reliable escalation core duties.
Capacity management is equally practical. The Lancet Commission on Global Surgery estimated that five billion people lack access to safe, affordable surgical care. Local managers cannot solve that gap alone. They can protect access by matching lists with demand, reducing avoidable cancellations, and measuring starts, turnover, overruns, and postponements. However, utilisation targets can mislead. A full list may hide exhausted teams, rushed checks, or fragile recovery capacity. Managers should question their dashboards, not worship them. That uncomfortable pause may prevent tomorrow’s cancellation—or today’s harm.
Operating theatre management is less about filling rooms than aligning people, time, and clinical priorities. A six-room unit may look efficient on paper. Yet one delayed anaesthetic review can shift every case. Staff coordination starts with a shared plan. Surgeons, anaesthetists, nurses, porters, and recovery teams need the same live information. Short huddles before the list expose gaps early. A missing instrument set or absent assistant should not appear at incision time. Too late.
Scheduling requires more than copying yesterday’s timetable. Managers should compare procedure duration, turnover time, cleaning needs, and staff competencies. A realistic schedule protects capacity without creating idle rooms. It also leaves space for urgent cases. Overbooking can increase overtime, fatigue, and rushed handovers. Underbooking wastes trained staff and valuable theatre hours. The difficult part is judging uncertainty. Procedure times vary, and optimistic estimates often fail. Reviewing actual start times and delays helps planners adjust future lists. Still, data does not explain every disruption. Human factors matter.
Capacity management should include recovery bays, sterile processing, beds, and transport. Opening another theatre is useless if recovery has no space. A live dashboard can show cancelled cases, room status, and staffing pressure. However, dashboards need accurate updates. Someone must own that task. In practice, teams sometimes record delays inconsistently, which weakens later analysis. Managers should invite staff to challenge the process without blame. A nurse may notice a bottleneck before any report does. Small changes, such as staggering breaks, can protect patient flow. They can also create new pressure elsewhere. That trade-off deserves regular review.
Operating theatre management depends on reliable routines, not good intentions alone. Every patient should receive an identity check, procedure confirmation, allergy review, and documented consent before anaesthesia begins. A brief team pause can prevent wrong-site surgery and reveal missing equipment. Small communication gaps matter. A rushed handover may leave critical information unclear.
Infection control requires constant attention to detail. Staff must perform hand hygiene at the correct moments and protect sterile fields during every procedure. Theatre temperature, air quality, instrument sterilisation, and cleaning records need regular verification. Supervisors should investigate contamination events without blame, then correct the process. Perfect compliance is difficult. That is an uncomfortable fact. Still, repeated shortcuts should never become normal practice. Regulatory compliance also requires accurate staff training records, maintenance logs, incident reports, and audit findings. Requirements vary by location, so managers should follow current national and facility policies.
Tips: Use a visible safety checklist, but never treat it as a substitute for judgement. Assign one person to monitor sterile practice during complex procedures. Review near misses during short team meetings. Check emergency equipment at the start of each shift. Keep records clear, dated, and easy to retrieve. Ask staff what feels unsafe; they often notice problems before formal audits do. Mistakes can happen. Silence makes them worse.
Operating theatre management is a daily balance between clinical readiness and financial discipline. The Lancet Commission on Global Surgery estimated 313 million surgical procedures occur worldwide each year. Each procedure depends on available instruments, sterile supplies, trained staff, and working equipment. A missing cable can delay an entire list.
Supply control needs more than counting boxes. Theatre teams should track usage by procedure, expiry dates, emergency stock, and opening waste. Practice Greenhealth reports that operating rooms may generate 20–30% of hospital waste. Unused opened packs are especially costly. Our first inventory forecast was wrong because it ignored surgeon preference and last-minute case changes. That mistake still deserves review.
Equipment management requires clear ownership. Maintenance records should show inspection dates, faults, loan units, and staff training. ECRI’s 2024 health technology report highlights risks linked to inadequate maintenance and insufficient user preparation. Costs also rise when equipment sits idle between cases. Simple dashboards can compare turnover time, utilization, cancellations, and repair delays. The numbers need context. A high utilization rate may hide exhausted staff or unsafe scheduling.
Labor remains a major operational resource. The 2024 NSI National Health Care Retention & RN Staffing Report recorded average registered-nurse turnover at 18.4%. Frequent turnover weakens local knowledge and increases onboarding costs. Cross-training helps, but it cannot replace realistic staffing plans. Some theatres still measure speed more carefully than readiness. That is an uncomfortable gap.
Operating theatres must balance clinical safety, staff availability, equipment readiness, supply continuity, cost control, and efficient use of surgical capacity.
The chart presents commonly used perioperative management benchmarks: on-time first-case starts of at least 85%, operating-room utilization around 80%, same-day cancellation rates below 5%, turnover times of 30 minutes or less, and instrument or equipment availability of at least 98%. Actual targets vary by hospital, specialty, and case mix.
Reference framework: perioperative efficiency and patient-flow guidance from AORN, NHS England, and peer-reviewed operating-room management research.
Operating theatre management depends on accurate performance measurement and practical responses to daily disruption. Useful indicators include first-case on-time starts, room utilisation, turnover duration, cancellation rates, and delayed discharges. Numbers alone are not enough. A ten-minute delay may reflect missing instruments, late consent, or an unavailable bed. Each cause needs separate review.
I have seen teams improve reliability by checking the operating list at several points during the day. A short morning huddle can expose staffing gaps, equipment concerns, and complex cases. Theatre coordinators should record delays close to the event, while details remain clear. Staff feedback also matters. A dashboard may show poor turnover performance, but direct observation might reveal cleaning pressure or unclear handovers. Measurement can be uncomfortable. Some data will expose weak processes, not weak individuals.
Tips: Use a small set of agreed measures. Review trends weekly, not isolated incidents. Set realistic escalation points for cancellations and delays. Compare planned and actual times without blaming teams. Test one operational change for two weeks, then reassess its effect. Keep lessons visible. They are easily forgotten. Even experienced departments can overestimate their efficiency when exceptions are treated as normal.
A shared live plan keeps surgeons, anaesthetists, nurses, porters, and recovery teams aligned. Short huddles expose missing staff or instruments before incision. Not always early enough.
Include procedure length, cleaning time, turnover, staff skills, and possible delays. Leave capacity for urgent cases. Optimistic estimates often fail.
Overbooking can create overtime, fatigue, rushed handovers, and unsafe pressure. Underbooking wastes trained staff and room time. The balance is imperfect.
Capacity includes recovery bays, sterile processing, beds, transport, equipment, and staff. Opening another room helps little if recovery bays are full. The bottleneck may be elsewhere.
Confirm identity, procedure, allergies, consent, equipment, and site before anaesthesia begins. Use a short team pause. Small gaps matter.
Staff need correct hand hygiene, protected sterile fields, verified air quality, and reliable cleaning records. Instrument sterilisation requires regular checks. Shortcuts should not become routine.
Track usage, expiry dates, emergency stock, maintenance, faults, and staff training. A missing cable can delay an entire surgical list. Boxes alone tell little.
Compare procedure usage, opened-pack waste, turnover time, cancellations, repairs, and room utilization. High utilization may hide exhausted staff. The numbers need context.
Frequent turnover weakens local knowledge and increases training demands. Cross-training helps, but it cannot replace realistic staffing plans. Speed is not readiness.
Operating theatre management involves coordinating people, processes, resources, and clinical priorities to deliver safe and efficient surgical care. What are common challenges in operating theatre management? Key difficulties include defining responsibilities clearly, balancing staff availability with changing surgical schedules, and making the best use of limited theatre capacity. Effective managers must also support communication among surgeons, nurses, anaesthesia teams, patients, and administrative staff while reducing delays and unnecessary cancellations.
Patient safety remains central to every operational decision. Theatre managers need to maintain strong infection prevention practices, follow regulatory requirements, and ensure that equipment and supplies are available, functional, and properly maintained. At the same time, they must monitor costs, manage resources responsibly, and respond quickly to unexpected staffing, equipment, or scheduling problems. Regular performance measurement, using indicators such as utilisation, turnover time, cancellations, and safety outcomes, helps identify weaknesses and guide practical improvements. A coordinated, adaptable, and data-informed approach can improve both theatre efficiency and the quality of patient care.

Suffolk Medical